Skip to content
In Stock Arimidex
Breast Cancer

Arimidex

Lower oestrogen exposure can reduce hormonal stimulation of sensitive cancer cells. Treatment decisions depend on tumour receptor status, menopausal status, previous treatment and the oncology plan.

Guaranteed quality Original product
Delivery: from 4 days Discreet shipping
24/7 Support Always available
Active ingredient: Anastrozole
Select pack Package Per unit Price
$ 11.51 $ 345.32
Free Express Delivery $ 9.40 $ 690.64 $ 564.26 Save 18%
Best value Free Express Delivery $ 8.72 $ 1,035.96 $ 784.98 Save 24%

Free delivery on orders from $ 356.00, free express delivery from $ 534.00

Secure payment methods:
VISA AMEX JCB DISCOVER

Lower oestrogen exposure can reduce hormonal stimulation of sensitive cancer cells. Treatment decisions depend on tumour receptor status, menopausal status, previous treatment and the oncology plan.

Product information

Arimidex reduces oestrogen production by blocking aromatase, an enzyme involved in making oestrogen after menopause. Its active ingredient, anastrozole, is used mainly for hormone receptor-positive breast cancer in postmenopausal women.

Ingredients

Arimidex contains anastrozole and belongs to the aromatase inhibitor class. It is an oral tablet used in selected breast cancer treatment plans, with the strength and formulation shown in the product card above. Treatment decisions depend on tumour receptor status, menopausal status, previous treatment and the oncology plan.

Active Ingredient and Drug Class

Anastrozole is the active ingredient in Arimidex. Aromatase inhibitors reduce the body’s production of oestrogen rather than blocking oestrogen receptors directly. The medicine is used in hormone therapy for selected breast neoplasms, including hormone receptor-positive primary and metastatic breast cancer.

The product name and active ingredient describe different things: Arimidex is the product name, while anastrozole is the medicine responsible for the pharmacological effect.

Keep a current list of every prescription medicine, over-the-counter product and supplement used during cancer treatment. The oncology team needs this information before changing endocrine therapy.

Breast Cancer Receptor Status

Pathology testing identifies receptors on breast cancer cells. Oestrogen receptor-positive breast cancers can use oestrogen signalling to support tumour growth, so reducing oestrogen may form part of the treatment strategy.

Arimidex is not appropriate for every breast cancer diagnosis. The pathology report, menopausal status and treatment history guide the choice between hormone therapy, chemotherapy, radiotherapy, surgery and other oncology treatments.

Therapeutic indications

Anastrozole may be prescribed for primary breast cancer after surgery or other initial treatment. It may also be used in selected cases of metastatic secondary breast cancer, where the aim may be disease control and reduction of hormone-driven tumour activity.

Adjuvant Treatment for Primary Breast Cancer

Adjuvant treatment is therapy given after the main local treatment, such as surgery. Arimidex may be included when pathology shows a hormone-sensitive tumour and the person is postmenopausal or has a treatment plan that addresses ovarian hormone production.

The oncologist determines the sequence and duration. Some patients receive endocrine therapy after surgery, while others may receive it after chemotherapy or alongside additional treatments selected for their cancer type.

Treatment of Metastatic Breast Cancer

Metastatic breast cancer has spread beyond the original breast and nearby tissues. In selected patients, anastrozole can be used as hormone therapy to reduce oestrogen-driven stimulation and help control disease.

Treatment combinations vary. The oncology team may consider previous endocrine therapy, disease progression, symptoms, other medicines and the person’s general health before selecting a treatment plan.

Treatment setting Clinical purpose Main decision factors
Primary breast cancer Reduce the chance of hormone-sensitive disease returning after initial treatment Receptor status, stage, menopausal status and previous therapy
Metastatic secondary breast cancer Help control oestrogen-sensitive disease Previous treatment, progression, symptoms and the oncology plan

Directions for use

Arimidex is taken orally as prescribed. The amount per intake is set individually for each person rather than being one fixed number, so the prescribed instructions take priority over general dosing examples.

Routine Oral Use

  • Take the tablet at the prescribed interval, usually at the same time each day.
  • Swallow it as directed with water.
  • Follow the Australian Product Information or prescriber’s instructions about food.
  • Do not alter the tablet unless a pharmacist or prescriber confirms that doing so is suitable.
  • Continue treatment until the oncology team changes or stops it.

Do not double the next intake after a missed dose. If vomiting occurs soon after administration, contact the treating oncology service or pharmacist for specific advice rather than automatically repeating the tablet.

A phone reminder linked to a daily routine, such as breakfast or brushing your teeth, can reduce missed doses. Keep the reminder separate from food timing if your prescriber has given specific food instructions.

Missed Doses and Treatment Changes

A missed dose should not be replaced with two tablets unless a prescriber has explicitly instructed this. Individual advice may depend on how long ago the dose was missed and when the next dose is due.

Do not stop Arimidex because of joint pain, hot flushes or fatigue without reporting the problem. The treatment plan may allow symptom management, a supervised change or another approach.

When not to use it

Arimidex is not for you if:

  • You are pregnant or may be pregnant.
  • You are breastfeeding.
  • You have a known allergy to anastrozole or an ingredient in the tablet.
  • You are premenopausal and have not had the required specialist assessment of ovarian function.
  • You have a medical history that makes the planned endocrine treatment unsuitable.
  • You are taking medicines or supplements that could affect the oncology plan.

The prescriber must also review liver disease, osteoporosis, fracture history, cholesterol problems, unexplained vaginal bleeding and previous clotting events. Severe or unusual symptoms require prompt clinical assessment.

When this is not for you

Arimidex may not be suitable if you are pregnant, breastfeeding or still premenopausal without specialist assessment of ovarian function. It may also be unsuitable if you have an allergy to anastrozole, significant liver or bone problems, unexplained vaginal bleeding, a history of clotting events or medicines and supplements that could interfere with your cancer treatment. Do not start, stop or change treatment without speaking with the oncology team.

Unwanted effects

The most common tolerability issues relate to reduced oestrogen. Symptoms vary between patients and can change during treatment.

Common Oestrogen-Reduction Effects

Possible effects include:

  • Hot flushes and sweating.
  • Joint stiffness or pain.
  • Muscle aches.
  • Tiredness.
  • Vaginal dryness.
  • Reduced libido.
  • Mood changes.
  • Headache or nausea.
  • Sleep disturbance.

Persistent joint pain deserves attention. Quietly missing tablets can reduce treatment continuity, while a review may identify physiotherapy, exercise changes, analgesia, treatment timing or another clinical option.

Record the location, severity and timing of joint symptoms for one to two weeks. A short symptom diary gives the oncology team more useful information than simply saying that the tablets caused aches.

Bone Health and Long-Term Monitoring

Lower oestrogen can reduce bone mineral density and increase fracture risk over time. The risk is more relevant in people with osteoporosis, previous fractures, low body weight, limited mobility or other factors affecting bone strength.

Clinical monitoring may include bone-density assessment, dietary review, weight-bearing activity and discussion of calcium or vitamin D. Bone medicines are prescribed only when the clinician considers them appropriate.

Blood Clots, DVT and Pulmonary Embolism

A blood clot is a possible medical concern, although clot risk is more strongly associated with tamoxifen than with aromatase inhibitors. Deep vein thrombosis, or DVT, can cause one-sided leg swelling, warmth, redness or pain. A clot that travels to the lungs can cause a pulmonary embolism.

Seek emergency help in Australia for sudden breathlessness, chest pain, fainting, rapid breathing or coughing blood. These symptoms need urgent assessment and should not be managed by waiting for the next routine oncology appointment.


Mechanism of action

Aromatase is an enzyme that helps convert other hormones into oestrogen. After menopause, much of the body’s oestrogen is produced through this peripheral conversion in tissues such as fat and muscle rather than directly by the ovaries.

Anastrozole inhibits aromatase. This lowers exposure to oestrogen, including estradiol, a major form of oestrogen. In an oestrogen receptor-positive tumour, less hormonal stimulation can slow the growth of cancer cells. The treatment does not directly destroy cancer cells and does not replace surgery, radiotherapy or chemotherapy when those treatments are indicated [1]. Clinical response still depends on tumour biology, treatment setting and the wider oncology plan.

Aromatase Inhibition and Oestrogen Reduction

The process can be described in three steps:

  • Aromatase converts hormone precursors into oestrogen.
  • Anastrozole inhibits aromatase.
  • Lower oestrogen signalling reduces stimulation of sensitive cancer cells.

Aromatase inhibition is strongest after menopause because ovarian oestrogen production has already declined. Estradiol levels can fall substantially, though the aim is not to remove every trace of oestrogen from the body.

Hormonal Dependence of ER-Positive Tumours

Laboratory testing determines whether a tumour expresses oestrogen receptors. An ER-positive result means that oestrogen signalling may influence the cancer’s behaviour. The oncology team combines this result with tumour stage, grade, lymph-node findings and other pathology details when selecting treatment.

Reduced oestrogen does not guarantee the same response in every person. Cancer biology varies, and endocrine treatment forms one part of a wider care plan.

Common mistakes

Patients sometimes interpret joint pain as proof that the medicine is damaging every joint, then stop treatment without advice. Symptoms can have several causes, and early assessment may allow practical management.

Another mistake is assuming that a missed tablet should be replaced by a double dose. It should not. The correct action depends on the timing of the missed dose and the next scheduled dose.

Some patients also overlook new vaginal bleeding after menopause, expecting all reproductive symptoms to disappear during endocrine treatment. That symptom needs review, even when it is light or occurs only once.

Finally, ovarian suppression and aromatase inhibition are not the same treatment. A premenopausal patient should not start or stop ovarian suppression independently.

Comparison

Arimidex and tamoxifen both belong to hormone therapy, but they work at different points in the oestrogen pathway.

Anastrozole is an aromatase inhibitor. It reduces oestrogen production. Tamoxifen blocks oestrogen receptors in breast tissue, preventing oestrogen from activating those receptors. Neither option is universally preferable; the choice depends on clinical factors and tolerability.

Therapy Main mechanism Clinical considerations
Anastrozole Inhibits aromatase and lowers oestrogen production Often considered after menopause; bone health and joint symptoms require attention
Tamoxifen Blocks oestrogen receptors in breast tissue Can be used in different menopausal settings; clot and uterine risks require clinical review

Arimidex and Tamoxifen Mechanisms

Anastrozole acts upstream by reducing oestrogen formation. Tamoxifen acts at the receptor level. This distinction explains why their adverse-effect profiles differ.

Arimidex is associated with low-oestrogen effects such as joint symptoms and bone loss. Tamoxifen has a different risk pattern, including venous thromboembolism and endometrial changes. The oncology team weighs recurrence risk, bone density, clot history, uterine health, menopausal status and previous treatment [2].

Treatment Selection Factors

Discussion with the oncology team may include:

  • Bone density and previous fractures.
  • Personal or family history of blood clots.
  • Menopausal status and ovarian function.
  • Previous tamoxifen or aromatase inhibitor treatment.
  • Joint symptoms, mobility and existing arthritis.
  • Liver disease, cholesterol problems and other chronic conditions.
  • Medicines, vitamins and herbal supplements.

What doctors say

In oncology practice, the first decision is usually whether the tumour is hormone receptor-positive and whether the patient’s menopausal status supports aromatase inhibitor treatment. Arimidex is not selected solely because a person has breast cancer; pathology and treatment history determine whether it fits the plan.

Doctors also focus on persistence. Joint pain, vaginal symptoms and hot flushes can be manageable, but they should be reported early. A patient who stops treatment silently may lose the opportunity to receive targeted symptom support or a supervised change in endocrine therapy.

One practical point is often missed: menopausal status can be less obvious after chemotherapy, hysterectomy or irregular menstrual cycles. The oncology team may need clinical information and selected tests before deciding whether aromatase inhibition alone is suitable.

What customers often ask

Can Arimidex be used during pregnancy or breastfeeding?

No. Arimidex is not intended for use during pregnancy or breastfeeding because it lowers oestrogen and may harm a developing pregnancy or nursing infant. The 2024 TGA Australian Product Information identifies pregnancy and lactation as situations requiring avoidance and specialist management. Contraception and pregnancy planning should be discussed with the oncology team before treatment begins [3].

Can the Arimidex tablet be split, crushed or chewed?

The tablet should be swallowed as directed rather than split, crushed or chewed without specific advice. Altering a tablet can affect accurate dosing or make administration difficult, even when the medicine is not a modified-release product. The 2024 TGA and the pharmacist can provide formulation-specific instructions when swallowing is difficult, especially after surgery or during treatment-related nausea. A pharmacist can also check whether an alternative administration approach is appropriate.

Is alcohol permitted while using Arimidex?

Alcohol is not known to directly cancel the aromatase-inhibiting action of anastrozole, but it can worsen hot flushes, sleep disruption, dizziness or fatigue. Alcohol may also complicate liver assessment in people with liver disease or other medicines affecting the liver. Cancer Council Australia’s 2024 guidance advises discussing alcohol intake within the wider cancer treatment plan, with individual guidance from the treating team.

Which concrete condition can rule out Arimidex?

Pregnancy rules out Arimidex use. A known allergy to anastrozole or a tablet ingredient also prevents treatment, while premenopausal status may require ovarian suppression or another endocrine strategy rather than anastrozole alone. The 2023 EMA product information describes these clinical boundaries and supports specialist assessment before treatment begins [4].

What should be discussed with a doctor before starting Arimidex?

Tell the prescriber about osteoporosis, previous fractures, arthritis, liver disease, high cholesterol, unexplained vaginal bleeding, clotting history and current medicines. Menopausal status and the tumour’s oestrogen-receptor result are central treatment considerations. The 2024 TGA recommends reviewing relevant medical history and concomitant treatment before prescribing, with follow-up adapted to the patient’s risks.

Can Arimidex be combined with other medicines or supplements?

All anticoagulants, hormone-containing products, calcium or vitamin D supplements, herbal products and regular pain medicines should be discussed with the oncology team. The issue is not that every combination is forbidden; the concern is that another product may alter treatment decisions, bone management, liver monitoring or symptom control. The 2023 WHO cancer-treatment framework supports coordinated medication review during systemic therapy [5].

Do you offer anonymous delivery?

Your order will be securely packed and shipped within 24 hours. This is exactly what your package will look like (images of an actual item sent). It has the size and look of a regular private letter (24x11x0.7 cm) and its contents cannot be seen.

Comparison

Arimidex Current

Active ingredient: Anastrozole
1mg
From $ 345.32
pills
4.3 (4)

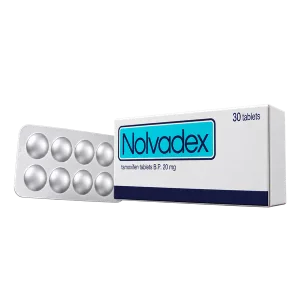
Nolvadex

Active ingredient: Tamoxifen
10mg 20mg
From $ 158.42
pills
4.2 (3)

How the medicines for Breast Cancer compare

Sources

  1. European Medicines Agency (2024). Arimidex: Summary of Product Characteristics and Product Information
  2. Early Breast Cancer Trialists’ Collaborative Group (2015). Aromatase inhibitors versus tamoxifen in early breast cancer: patient-level meta-analysis of the randomised trials
  3. Therapeutic Goods Administration (2024). Arimidex (anastrozole) Australian Product Information
  4. European Medicines Agency (2023). Anastrozole-containing medicinal products: product information
  5. World Health Organization (2023). WHO Classification of Tumours: Breast Tumours

How Buyers Rate Arimidex

Based on 4 reviews

Graham, 64 Verified
Rating: 3.5 out of 5

I had been taking Arimidex for several months after surgery. The hot flushes were manageable, but the stiffness in my hands was worse in the morning. Gentle movement helped, and reporting it meant the clinic could discuss options instead of me stopping the tablets.

Several months 5 Oct 2026
Ben N., 40 Verified
Rating: 5 out of 5

I was premenopausal when the treatment was first discussed, so the oncology team explained ovarian suppression carefully. I had assumed anastrozole alone would switch off ovarian hormones. That clarification changed how I understood the treatment.

20 Oct 2026
Adam, 26 Verified
Rating: 5 out of 5

I missed a dose during a busy week and nearly took two tablets the next morning. The pharmacist told me not to double it and helped me work out how to return to the prescribed schedule. I also started using a reminder.

23 Oct 2026
James, 56 Verified
Rating: 3.5 out of 5

The medicine itself was straightforward, but fatigue and sleep problems became frustrating after several weeks. I did not feel comfortable stopping treatment, so I raised it at review. The discussion was more useful than trying to manage it alone.

Several weeks 2 Nov 2026
Get our free app Shop faster and track your orders 3.8 · 491 reviews Install