Skip to content
In Stock Metformin
Diabetes

Metformin

Metformin hydrochloride is a biguanide tablet used mainly for people with type 2 diabetes. It helps improve blood-glucose control by reducing glucose production by the liver and improving the body’s…

Guaranteed quality Original product
Delivery: from 4 days Discreet shipping
24/7 Support Always available
Active ingredient: Metformin
Select dosage:
Select pack Package Per unit Price
$ 7.30 $ 72.98
$ 4.09 $ 145.96 $ 81.88 Save 44%
$ 3.03 $ 218.94 $ 90.78 Save 59%
$ 1.66 $ 437.88 $ 99.68 Save 77%
$ 1.50 $ 656.82 $ 135.28 Save 79%
$ 1.35 $ 875.76 $ 161.98 Save 82%
$ 1.19 $ 1,313.64 $ 213.60 Save 84%
$ 1.05 $ 1,970.46 $ 284.80 Save 86%
Best value $ 0.94 $ 2,627.28 $ 339.98 Save 87%
$ 2.02 $ 60.52
$ 1.13 $ 121.04 $ 67.64 Save 44%
$ 0.83 $ 181.56 $ 74.76 Save 59%
$ 0.73 $ 242.08 $ 87.22 Save 64%
$ 0.62 $ 363.12 $ 112.14 Save 69%
Best value $ 0.52 $ 726.24 $ 188.68 Save 74%

Free delivery on orders from $ 356.00, free express delivery from $ 534.00

Secure payment methods:
VISA AMEX JCB DISCOVER

Metformin hydrochloride is a biguanide tablet used mainly for people with type 2 diabetes. It helps improve blood-glucose control by reducing glucose production by the liver and improving the body’s response to insulin; the amount per intake is individualized.

Product information

Metformin contains metformin hydrochloride, a biguanide antidiabetic agent. The amount per intake is set individually for each person rather than being one fixed number. The medicine is used mainly for type 2 diabetes when the body does not use insulin efficiently or does not produce enough insulin to maintain normal blood-glucose levels.

This helps lower fasting and after-meal blood-glucose levels without directly stimulating the pancreas to release more insulin [1].

Ingredients

Metformin contains metformin hydrochloride, a biguanide antidiabetic agent. The amount per intake is set individually for each person rather than being one fixed number. The product is supplied as tablets in blister packaging.

Therapeutic indications

The medicine is used mainly for type 2 diabetes when the body does not use insulin efficiently or does not produce enough insulin to maintain normal blood-glucose levels.

Clinical use follows a broader diabetes plan:

  • regular blood-glucose monitoring;
  • suitable dietary intake;
  • physical activity appropriate for the person’s health;
  • scheduled kidney-function assessment;
  • review of other medicines that may affect glucose or hydration;
  • adjustment of treatment when glucose targets are not reached.

The World Health Organization identifies metformin as a standard medicine for type 2 diabetes management, while the Therapeutic Goods Administration regulates Australian medicine information and safety requirements.

Directions for use

The amount per intake is set individually for each person rather than being one fixed number. Treatment often begins with a lower amount and increases gradually when blood glucose remains above target and digestive symptoms are manageable. The prescriber considers kidney function, age, meal pattern, other medicines, and the selected formulation.

Typical administration principles include:

  • swallow the tablet with food or immediately after food;
  • take doses at consistent times each day;
  • swallow modified-release tablets whole;
  • do not take an extra tablet to compensate for a missed dose;
  • if a dose is missed, take the next scheduled dose at the usual time unless specific medical instructions say otherwise;
  • tell the prescribing clinician about vomiting, severe diarrhoea, dehydration, or reduced fluid intake.

A missed dose is usually left until the next planned dose rather than doubled. Taking two doses close together can intensify nausea, diarrhoea, abdominal discomfort, and other adverse effects.

If vomiting or diarrhoea prevents normal fluid intake, contact the prescriber promptly because dehydration can increase kidney-related risk while taking metformin.

The Australian Product Information approach places dose adjustment alongside renal assessment. The TGA also recognises that metformin treatment requires attention to conditions that may reduce kidney function or tissue oxygenation.

When not to use it

Metformin is not suitable for every person with diabetes. Treatment requires specific review when kidney function is reduced or when an acute illness could cause dehydration, poor oxygen delivery, or rapid clinical deterioration.

  • severe renal impairment or acute kidney injury;
  • current or previous lactic acidosis;
  • severe dehydration from vomiting, diarrhoea, fever, or poor fluid intake;
  • severe infection, shock, or a condition causing inadequate tissue oxygenation;
  • severe liver impairment or heavy alcohol exposure that increases metabolic risk;
  • a known allergy to metformin hydrochloride or an excipient in the tablets.

When this is not for you

This medication may not be right for you if you have serious kidney problems, severe dehydration, a severe infection, shock, serious liver disease, or heavy alcohol exposure. You should also tell your prescriber if you have had lactic acidosis or an allergy to metformin or any tablet ingredient.

Older adults and people taking medicines that affect renal blood flow may need closer monitoring. Tell the prescriber about insulin, sulfonylureas, diuretics, blood-pressure medicines, corticosteroids, thyroid medicines, and any treatment that may alter glucose or kidney function.

Unwanted effects

Nausea, loose stools, abdominal discomfort, bloating, and reduced appetite are common early effects. Some people notice a metallic taste. These reactions often appear after starting treatment or increasing the amount and may become milder as the digestive system adapts.

Metformin can cause diarrhoea even after months of stable treatment. A new persistent change deserves review because infection, food intolerance, bowel disease, and other medicines can produce similar symptoms.

The rare but serious complication is lactic acidosis. Urgent symptoms can include:

  • unusual severe weakness;
  • rapid or difficult breathing;
  • persistent vomiting;
  • severe abdominal discomfort;
  • unusual sleepiness or confusion;
  • feeling very cold;
  • a slow or irregular heartbeat.

Long-term metformin treatment can reduce vitamin B12 absorption in some people. Possible consequences of vitamin B12 deficiency include tiredness, pallor, sore or swollen tongue, numbness, pins and needles, balance problems, or cognitive changes.

The association between metformin and B12 reduction has been described in clinical research, including a long-term randomised study indexed in PubMed [2].

Mechanism of action

Metformin reduces glucose production by the liver and improves insulin sensitivity in peripheral tissues, including skeletal muscle, allowing more glucose to move from the bloodstream into cells. It may also reduce intestinal glucose absorption. Its action does not directly stimulate the pancreas to release insulin.

Common mistakes

Several everyday errors reduce tolerability or make glucose readings difficult to interpret:

  • taking the tablet before eating despite repeated stomach upset;
  • doubling the next dose after forgetting one;
  • crushing a modified-release tablet;
  • stopping treatment during a short illness without giving the prescriber relevant information;
  • failing to mention vomiting, diarrhoea, dehydration, or a planned contrast scan;
  • assuming that metformin alone prevents glucose rises after every high-carbohydrate meal;
  • ignoring persistent numbness or fatigue that could suggest vitamin B12 deficiency;
  • overlooking insulin or sulfonylurea use when discussing episodes of sweating, shaking, or confusion.
Keep a brief record of dose time, meal timing, digestive symptoms, and glucose readings during dose changes. Patterns are more useful than a single unusual reading.

One practical detail is easy to miss: a new medicine can change glucose control without changing metformin itself. Corticosteroids, some diuretics, and acute infections may raise glucose, while insulin and secretagogues can lower it.

Comparison

The closest alternatives are not interchangeable simply because they are used for type 2 diabetes. Sulfonylureas increase insulin secretion and can cause hypoglycaemia. Insulin directly replaces or supplements insulin activity. Metformin mainly reduces liver glucose production and improves insulin sensitivity, so its benefits and risks differ.

What doctors say

In clinical practice, prescribers usually introduce metformin in a way that protects tolerability. A lower starting amount, gradual adjustment, and taking tablets with food can make the first weeks easier. A person who stops after one difficult day may miss the chance for symptoms to settle.

Doctors also assess the treatment response with more than one glucose reading. HbA1c shows average glucose over approximately two to three months, while home readings reveal daily patterns, meal effects, and possible low-glucose episodes when other medicines are involved.

Metformin is a treatment for glucose regulation, not a replacement for nutrition, activity, sleep, or follow-up. It may remain useful for years when kidney function stays suitable and the person continues to tolerate it. The European Medicines Agency describes metformin-containing medicines within the established treatment framework for type 2 diabetes.

A clinician would also review whether a new symptom reflects metformin, diabetes itself, another medicine, or a separate illness. Persistent numbness, ongoing diarrhoea, unexplained anaemia, and repeated low glucose require targeted assessment.

What customers often ask

Does Metformin cause diarrhoea?

Diarrhoea is a recognised gastrointestinal adverse effect of metformin, especially during initiation or dose escalation. The United States Food and Drug Administration describes gastrointestinal symptoms among the common reactions in prescribing information reviewed in 2022. Taking the tablet with food and increasing the amount gradually can improve tolerance, but persistent diarrhoea requires medical review because dehydration can affect kidney function.

How does Metformin differ from insulin or sulfonylureas?

Metformin mainly lowers liver glucose production and improves insulin sensitivity. Insulin supplies or replaces insulin activity, while sulfonylureas stimulate the pancreas to release more insulin. The World Health Organization’s 2023 diabetes guidance places these medicines within different therapeutic groups, with different effects on hypoglycaemia, body weight, and treatment monitoring.

Can Metformin affect driving, concentration, or machinery work?

Metformin alone does not usually impair alertness or coordination. The risk changes when it is combined with insulin or a sulfonylurea, because hypoglycaemia can cause dizziness, blurred vision, confusion, or delayed reactions. Guidance from the TGA in 2024 supports checking glucose patterns and recognising low-glucose symptoms before driving or operating machinery.

Can the tablet be split, crushed, or chewed?

A metformin tablet should be swallowed according to its formulation. Modified-release tablets should generally be swallowed whole because crushing or chewing can change the release pattern. The Therapeutic Goods Administration’s 2024 Australian Product Information gives formulation-specific administration instructions, so the tablet design determines whether splitting is appropriate.

Can Metformin be used by people under 18?

Metformin may be prescribed for some adolescents with type 2 diabetes, but treatment depends on age, diagnosis, kidney function, growth, and the clinical plan. It is not suitable for every child with abnormal glucose readings. The American Diabetes Association’s 2025 Standards of Care describe age-specific diabetes treatment, while paediatric prescribing requires individual assessment.

How should Metformin be stored at home and during travel?

Keep the tablets in a dry place at normal room temperature, away from excess heat and moisture. A bathroom cabinet may be unsuitable because steam and humidity can affect medicines. The TGA’s 2024 medicine-safety information supports keeping medicines in their supplied packaging during travel, carrying enough for the planned journey, and avoiding prolonged exposure to heat in a car.

Do you offer anonymous delivery?

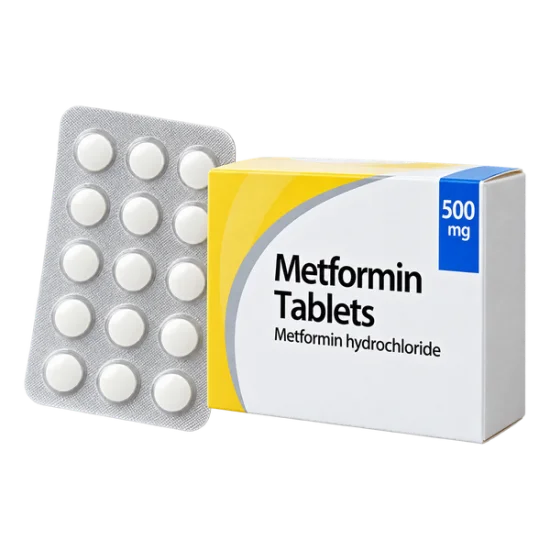
Your order will be securely packed and shipped within 24 hours. This is exactly what your package will look like (images of an actual item sent). It has the size and look of a regular private letter (24x11x0.7 cm) and its contents cannot be seen.

Comparison

Actos

Active ingredient: Pioglitazone
15mg 30mg 45mg
From $ 108.58
pills
4 (3)

Amaryl

Active ingredient: Glimepiride
2mg 3mg 4mg 1mg
From $ 149.52
pills
4.1 (5)

Empagliflozin

Active ingredient: Empagliflozin
10mg 25mg
From $ 332.86
pills
4.1 (5)

Forxiga

Active ingredient: Dapagliflozin
10mg 5mg
From $ 229.62
pills
4.3 (4)

Glucophage

Active ingredient: Metformin
1000mg 500mg 850mg 250mg
From $ 181.56
pills
3.9 (5)

Karela

Active ingredient: Karela
250mg
From $ 218.94
pills
3.5 (5)

How the medicines for Diabetes compare

Sources

  1. U.S. Food and Drug Administration (2022). Metformin hydrochloride prescribing information.
  2. PubMed (2010). Long term treatment with metformin in patients with type 2 diabetes and risk of vitamin B-12 deficiency: randomised placebo controlled trial.

How Buyers Rate Metformin

Based on 5 reviews

Christopher, 44 Verified
Rating: 4.5 out of 5

took a 500 mg tablet with his evening meal after his prescriber introduced metformin gradually. The first week brought loose stools, but the symptoms eased by the third week. He found that taking it halfway through dinner worked better than taking it before eating.

The first week to the third week 30 Oct 2026
Joanne, 49 Verified
Rating: 3.5 out of 5

used metformin alongside dietary changes for several months. Her fasting readings became more consistent, although she disliked a metallic taste during the first fortnight. The taste faded, but she still needed regular reminders to take the tablet with food.

Several months 3 Nov 2026
John, 54 Verified
Rating: 4 out of 5

started treatment with a 500 mg dose and experienced nausea after several days. He stopped taking it without arranging a review, then restarted only after discussing a slower adjustment plan. The second attempt was easier, but he said the first interruption delayed progress.

Several days 5 Oct 2026
Michelle, 60 Verified
Rating: 4 out of 5

had taken metformin for years when blood testing showed low vitamin B12. She had noticed tingling in her feet and initially assumed it was diabetes-related. After assessment, her treatment plan included B12 replacement and continued monitoring.

Years 18 Oct 2026
Gareth A., 52 Verified
Rating: 4 out of 5

used metformin with another glucose-lowering medicine. His glucose improved, but he experienced sweating and shakiness after missing lunch. The episode led to a review of the combination treatment and meal timing rather than an increase in metformin.

11 Oct 2026
Get our free app Shop faster and track your orders 3.8 · 491 reviews Install